by Dr. Seth Langston | Feb 8, 2023 | Health Conditions, Labor and Delivery
“When faced with preterm delivery, expectant parents generally meet the NICU team before the
delivery in the form of a prenatal consult. This consultation allows the NICU care team to discuss the NICU’s role at the time of delivery, commonly encountered problems preterm babies face, and the risks and general outcomes expected at the anticipated gestational age. The level of detail provided can be entirely dependent on what the family wants to know. “
Imagine you’re 30 weeks pregnant and your water breaks. You call your doctor and are instructed to go to the hospital as you may be in preterm labor. Perhaps you’re at 25 weeks gestation and your blood pressure is too high, a concern for the pregnancy-related disorder pre-eclampsia. Again, your doctor insists you go to the hospital for inpatient monitoring. Despite multiple medications to lower your blood pressure it remains elevated, and you are told the next best option for both mother and baby is to deliver. These scenarios occur regularly. Nobody expects to have a preterm baby and to say it’s an overwhelming experience is an understatement. However, with modern day health care and the neonatal intensive care unit (NICU), a preterm baby can have an exceptional life characterized by bravery and resiliency.
Approximately 15 million preterm babies are born annually worldwide. The causes for preterm
delivery are vast and are generally considered to be from either maternal (the mother) or fetal (the baby) causes. Preterm babies are those born before 37 weeks gestation with the youngest known to have survived being 22 weeks. When born at the earliest of ages and smallest of sizes, preterm babies have some of the largest hurdles to overcome. This includes babies born at the edge of viability, known as periviable, and encompasses those born between 22- and 24-weeks gestation. Prematurity at these extremes requires thoughtful and serious conversations, but these babies can go on to survive and thrive. On the opposite end of the spectrum are late-preterm infants, which are born between 34 weeks and 36 weeks and 6 days. These babies are expected to do quite well but have their own set of challenges. In best case scenarios, a 35 or 36-week baby may not require admission to the NICU, while those born at 34 weeks generally require some assistance and monitoring in the NICU.
When faced with preterm delivery, expectant parents generally meet the NICU team before the delivery in the form of a prenatal consult. This consultation allows the NICU care team to discuss the NICU’s role at the time of delivery, commonly encountered problems preterm babies face, and the risks and general outcomes expected at the anticipated gestational age. The level of detail provided can be entirely dependent on what the family wants to know. Some families rely on statistics and numbers to feel more informed whereas other families seek generalizations to feel at ease. However, most families share similar concerns:
“Will my baby survive? Will my baby be okay?”
“What are the risks of delivering this early?”
“What will my baby’s future development be like? How will they be affected?”
“How long will my baby be in the NICU? Can I visit?”
“How will I breastfeed? Will I be able to do skin-to-skin?”
The answers to some of these questions are dependent on co-existing pregnancy complications, the gestational age of the baby, and estimated weight at time of delivery. Preterm infants require care in the NICU because of developmental immaturity. This can cause issues with breathing and feeding, unstable blood sugars, inability to maintain body temperature, jaundice, and even infections. Answers regarding outcomes such as survival and development are provided from local, national, and even global outcomes observed in preterm babies. Although we have a lot of information at our hands, it’s important to keep in mind that so much of what ultimately affects a preterm baby’s outcome is how they do following delivery and while in the NICU.
It can feel disempowering to have a preterm baby. Your birth plan and expectations suddenly change and necessary decisions you never thought about are suddenly at the doorstep. A team of medical professionals cares for your baby instead of you. There are tubes and wires you never thought you’d see attached to your baby. It’s an adjustment and may not be an easy one. However, families are supported every step of the way in the NICU and encouraged to be actively involved in their child’s care. Resources include social workers and family support groups that consist of previous patients’ families. Parents are encouraged to participate in daily care of their baby, including temperature checks and diaper changes. When medically feasible, skin-to-skin is highly encouraged, allowing for a bit of the normalcy expected after having a baby. Although the doctors and nurses know the medical side, parents know their babies and have as important a voice and opinion in the care their baby receives.

Having a preterm baby can be a rollercoaster ride: There are good days in the NICU and there are bad days; sometimes it feels like your baby takes two steps forward and three steps back. This is normal and something most preterm babies must deal with. Know they are doing their best and just need a little support to cross that finish line of going home. We celebrate the small victories and achievement of various milestones. For the staff, watching preterm babies meet the milestones needed to be discharged from the NICU is a privilege. After weeks to months of managing the challenges of prematurity in the NICU, having a baby graduate is a victory for everyone, but especially the family. Once home, they’ll generally follow-up in a clinic for NICU graduates to closely watch growth and development. The relationships and connections families form with the staff and other families lasts beyond the NICU, providing a lifelong network and support system. Although having a preterm baby may be frightening, there is a dedicated team to help guide you and your family through the process and deliver the highest quality of care. There is a reason preterm babies are referred to as warriors and heroes. Their uphill climb is tough and filled with obstacles, but they can persevere and show they’re able to thrive.

Seth Langston is a board-certified neonatologist currently working in Los Angeles, CA. Originally from Houston, TX he moved to Southern California for medical training and couldn’t seem to leave. His scholarly pursuits include teaching medical students and residents, as well as studying and minimizing health disparities within neonatology. In his free time, you will find him exploring good eats in Los Angeles, learning Italian, or working in the garden.

by Keira Moré | Oct 19, 2022 | Health Conditions, Labor and Delivery
Once we received news of the surgery, the rest was an agonizing blur. We were pushed upstairs to sign paper after paper with the anesthesiologist, releasing them of responsibility if they accidentally killed my baby. Having my newborn go through invasive surgery at only days old was one of the scariest things I have ever experienced.
A premonition

The sterile stillness of the hospital swallows me as I peer into the box. My newborn daughter is in the incubator, and there is something wrong. I feel powerless. As I reach over to grab her, I am jolted from my sleep and I wake up. During my pregnancy, this eerie nightmare plagued my sleep. I woke up unsettled and terrified each time. I prayed for a boy to prevent the unsettling nightmare from turning into a premonition. Little did I know, the birth of my first child would forever change my life in more ways than one.
My husband and I kept the gender of our child a surprise, planning to find out at birth. At 39 weeks, I was induced since I had signs of preeclampsia. After 24 hours of labor, my daughter arrived eagerly into this world. I was exhausted, but our first few moments together were magical. Once we were in the recovery room, I placed Valentina into the bassinet for a brief moment. When I looked over, I was paralyzed with fear. She had turned completely blue. As I shouted for the nurse, an eerie feeling of deja-vu washed over me.
The nurse struck the code-blue button on the wall, and Valentina was rushed to the nurse’s station. Since my daughter arrived quickly, she had an unsafe amount of amniotic fluid coating her lungs. I watched as the nurses struggled to put a tube down her tiny throat to suck out the remaining liquid. I have the gift of remaining calm and cool-headed during high-stress situations, but watching the hospital staff struggle was incredibly painful. It felt as if a part of me was now outside of myself, and I had no control over anything that happened. The nurses assured me that this was a relatively common procedure for babies who are born quickly, as the speed does not allow the pressure from the vaginal canal to drain the baby of the remaining fluid. Thankfully, our baby made a quick recovery. Later that day we were released from the hospital and were ecstatic to finally go home with our sweet Valentina.
Home from the hospital
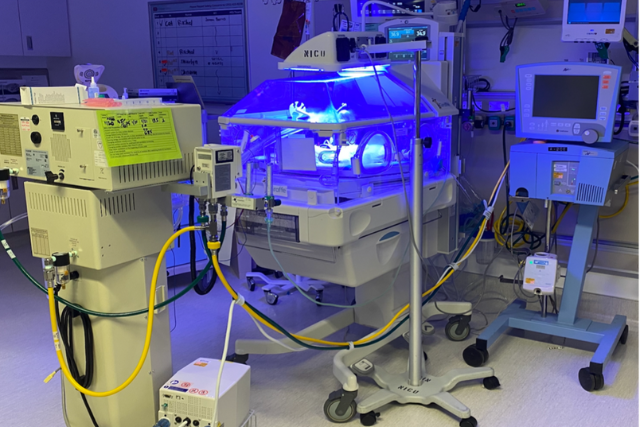
Our time at home together was short-lived. Soon after we arrived, I was called and told to bring Valentina back to the hospital as she had jaundice. Much later I learned that jaundice can be treated from home. Returning to the hospital was disorienting. Valentina was placed in an incubator for over 16 hours under blinding lights. At the same time, my milk had started to come in. I had to pump, but I was not allowed to feed her. At a time when all I wanted to do was hold her, I could only watch. Finally, we were told that we could go home again, and I was grateful to finally be able to just be with my daughter.
My relief was temporary. The next day, every time I tried to feed Valentina she vomited green. I was terrified, and quickly contacted my pediatrician and talked to my night nurse. My pediatrician claimed I had probably overfed her, while my night nurse reassured me that it was the green juice I had earlier which could affect the color of breast milk. I was confused and exhausted, but I placed my faith in their expertise. Valentina continued to vomit green over the next few days every time I tried to feed her. The more I desperately sought answers, the more I only received questions. I grew exceedingly nervous and restless. At the same time, I noticed she was sleeping in longer intervals, which did not seem normal to me. I could no longer take it, and on the fifth day, I called my pediatrician. I told him I was either bringing Valentina directly to him or back to the hospital.
When we arrived at the pediatrician’s office, the doctor noted her belly was distended, and confirmed she was lethargic. My pediatrician told my husband and me to take Valentina to the ER with a request to run a specific test. Being back at the hospital again and on the ER floor with Valentina was traumatizing. It was the last place I ever imagined I would be with my less-than-a-week-old daughter. My autonomy over myself and my daughter had been ripped away from me. My interactions with hospital staff were strained. The more I advocated for my daughter and myself, the more I was met with resistance and judgment. My anxiety peaked as the hospital ran test after test with no results, every test except the one my pediatrician had requested. Finally, after exhausting all other test options, they ran that one.
The test revealed that Valentina had an obstruction between her esophagus and stomach, known as duodenal atresia. The obstruction was just big enough to let in a drop of liquid at a time, which is why once my milk changed from colostrum to mature milk, she was unable to take it and instead, threw everything up. We were told that the only way to treat duodenal atresia was surgery. She would be cut open and they would have to create a bypass, creating a bigger opening inside her tiny body. There was a 15% chance that she would eventually need a second surgery.
Get the latest Informed Pregnancy news on Instagram!
A three hour surgery
Once we received news of the surgery, the rest was an agonizing blur. We were pushed upstairs to sign paper after paper with the anesthesiologist, releasing them of responsibility if they accidentally killed my baby. Having my newborn go through invasive surgery at only days old was one of the scariest things I have ever experienced. After a three-hour surgery, the surgeon stepped out to give us an update. He told me that they had cut open Valentina’s tiny body and removed her appendix. The surgeon had to rearrange her organs. I was livid. The surgeon had never asked my permission, and now all I could do was listen to what had happened to her. The pain was unbearable. He told us that Valentia had been admitted to the NICU.
While Valentina was in the NICU for recovery during the next few weeks I hated to be pulled away from her side. As a full-term baby, having her in the NICU amongst premature babies was unsettling. The recovery was painful. Due to the intensity of the surgery, I could not hold or feed her. The only thing I could do was watch. I felt helpless and powerless. For five days she received her nutrients from an IV. We would spend 14-16 hours a day at the NICU, leaving only to sleep because it was not allowed there. Despite the supportiveness of my family and friends, I perceived any attempt at asking me to leave the hospital as taking me away from my daughter. My time in the NICU was isolating, as I could not communicate my experience to others who had never felt the pain of such a quick separation from their newborn child.
A healthy daughter and a new career

Today, I am grateful that Valentina is a happy and healthy four-year-old. She has not needed a second surgery but her birth changed my experience not just as a mother, but as an advocate for others. Long after the surgery, I learned that duodenal atresia was a condition that should have been caught during my pregnancy as it is often a marker for chromosomal issues and Down’s Syndrome but my doctor made a mistake. He missed it entirely. While knowing in advance would not necessarily have made my experience easier, the shock and pain I experienced at finding out immediately after Valentina’s birth was scarring. In addition, I eventually learned the reason her vomit was green was due to bile, which as a new parent experiencing heightened emotions I did not realize at the time. There was so much information I didn’t know. I was so focused on advocating for my daughter, that I did not realize no one was advocating for me. The impact of Valentina’s surgery on my health embedded itself in my existence for a long time. After her birth, I needed to attend therapy and started medication for anxiety. I lived in constant fear and anxiety for my daughter, that anything could happen to her.
While a birth journey is wildly beautiful, it can at the same time be scary, intense, and a road riddled with unknowns. My journey with Valentina changed me. I realized that you have to be your best advocate, but that you should not have to do it alone. Our medical system does not present options to expectant parents, often diminishing their judgment and intuition about their own children. Oftentimes, expecting parents are unaware of all the choices they can make. Thus with the birth of Valentina, my dream to be a doula was also born. The isolation and pain I experienced after Valentina’s birth is something I never want another parent to experience. My connection with my daughter is one of the most magical and beautiful things I have in my life. As a doula, I want to help parents trust their connections with their children. My mission is to educate and empower other expectant parents so that they have the wealth of knowledge and tools to make the best decisions for themselves and their families. My long-term hope is to create an empowered, informed, supportive loving community
Learn how to get your breast pump covered by insurance on this popular episode of The Informed Pregnancy Podcast!

Keira Morè is a doula, childbirth educator, lactation educator, NICU peer mentor, wife, and mother to two beautiful children. Pivoting from a career in the fashion industry, her powerful experiences with the birth of her first child inspired her to become a doula. Experiencing firsthand the inequities and limitations of the medical system as a parent transformed Keira’s perspective of parenthood. With her work as a doula, Keira infuses compassion and integrity to empower birthing people and their families. She centers her work on informing and educating expectant parents so that each family can make decisions that best serve them. Currently, Keira resides in Los Angeles with her lovely family. During her downtime, she is building a beautiful garden with the help of two very avid little gardeners. Connect with Keira through her Instagram – @noa.doula
