by Dr. Seth Langston | Feb 8, 2023 | Health Conditions, Labor and Delivery
“When faced with preterm delivery, expectant parents generally meet the NICU team before the
delivery in the form of a prenatal consult. This consultation allows the NICU care team to discuss the NICU’s role at the time of delivery, commonly encountered problems preterm babies face, and the risks and general outcomes expected at the anticipated gestational age. The level of detail provided can be entirely dependent on what the family wants to know. “
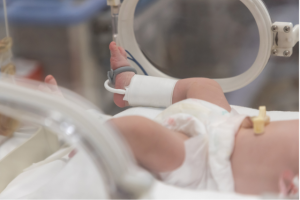
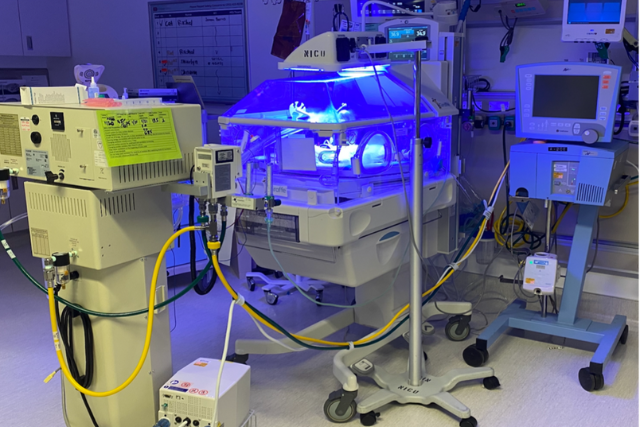
Imagine you’re 30 weeks pregnant and your water breaks. You call your doctor and are instructed to go to the hospital as you may be in preterm labor. Perhaps you’re at 25 weeks gestation and your blood pressure is too high, a concern for the pregnancy-related disorder pre-eclampsia. Again, your doctor insists you go to the hospital for inpatient monitoring. Despite multiple medications to lower your blood pressure it remains elevated, and you are told the next best option for both mother and baby is to deliver. These scenarios occur regularly. Nobody expects to have a preterm baby and to say it’s an overwhelming experience is an understatement. However, with modern day health care and the neonatal intensive care unit (NICU), a preterm baby can have an exceptional life characterized by bravery and resiliency.
Approximately 15 million preterm babies are born annually worldwide. The causes for preterm
delivery are vast and are generally considered to be from either maternal (the mother) or fetal (the baby) causes. Preterm babies are those born before 37 weeks gestation with the youngest known to have survived being 22 weeks. When born at the earliest of ages and smallest of sizes, preterm babies have some of the largest hurdles to overcome. This includes babies born at the edge of viability, known as periviable, and encompasses those born between 22- and 24-weeks gestation. Prematurity at these extremes requires thoughtful and serious conversations, but these babies can go on to survive and thrive. On the opposite end of the spectrum are late-preterm infants, which are born between 34 weeks and 36 weeks and 6 days. These babies are expected to do quite well but have their own set of challenges. In best case scenarios, a 35 or 36-week baby may not require admission to the NICU, while those born at 34 weeks generally require some assistance and monitoring in the NICU.
When faced with preterm delivery, expectant parents generally meet the NICU team before the delivery in the form of a prenatal consult. This consultation allows the NICU care team to discuss the NICU’s role at the time of delivery, commonly encountered problems preterm babies face, and the risks and general outcomes expected at the anticipated gestational age. The level of detail provided can be entirely dependent on what the family wants to know. Some families rely on statistics and numbers to feel more informed whereas other families seek generalizations to feel at ease. However, most families share similar concerns:
“Will my baby survive? Will my baby be okay?”
“What are the risks of delivering this early?”
“What will my baby’s future development be like? How will they be affected?”
“How long will my baby be in the NICU? Can I visit?”
“How will I breastfeed? Will I be able to do skin-to-skin?”
The answers to some of these questions are dependent on co-existing pregnancy complications, the gestational age of the baby, and estimated weight at time of delivery. Preterm infants require care in the NICU because of developmental immaturity. This can cause issues with breathing and feeding, unstable blood sugars, inability to maintain body temperature, jaundice, and even infections. Answers regarding outcomes such as survival and development are provided from local, national, and even global outcomes observed in preterm babies. Although we have a lot of information at our hands, it’s important to keep in mind that so much of what ultimately affects a preterm baby’s outcome is how they do following delivery and while in the NICU.
It can feel disempowering to have a preterm baby. Your birth plan and expectations suddenly change and necessary decisions you never thought about are suddenly at the doorstep. A team of medical professionals cares for your baby instead of you. There are tubes and wires you never thought you’d see attached to your baby. It’s an adjustment and may not be an easy one. However, families are supported every step of the way in the NICU and encouraged to be actively involved in their child’s care. Resources include social workers and family support groups that consist of previous patients’ families. Parents are encouraged to participate in daily care of their baby, including temperature checks and diaper changes. When medically feasible, skin-to-skin is highly encouraged, allowing for a bit of the normalcy expected after having a baby. Although the doctors and nurses know the medical side, parents know their babies and have as important a voice and opinion in the care their baby receives.

Having a preterm baby can be a rollercoaster ride: There are good days in the NICU and there are bad days; sometimes it feels like your baby takes two steps forward and three steps back. This is normal and something most preterm babies must deal with. Know they are doing their best and just need a little support to cross that finish line of going home. We celebrate the small victories and achievement of various milestones. For the staff, watching preterm babies meet the milestones needed to be discharged from the NICU is a privilege. After weeks to months of managing the challenges of prematurity in the NICU, having a baby graduate is a victory for everyone, but especially the family. Once home, they’ll generally follow-up in a clinic for NICU graduates to closely watch growth and development. The relationships and connections families form with the staff and other families lasts beyond the NICU, providing a lifelong network and support system. Although having a preterm baby may be frightening, there is a dedicated team to help guide you and your family through the process and deliver the highest quality of care. There is a reason preterm babies are referred to as warriors and heroes. Their uphill climb is tough and filled with obstacles, but they can persevere and show they’re able to thrive.

Seth Langston is a board-certified neonatologist currently working in Los Angeles, CA. Originally from Houston, TX he moved to Southern California for medical training and couldn’t seem to leave. His scholarly pursuits include teaching medical students and residents, as well as studying and minimizing health disparities within neonatology. In his free time, you will find him exploring good eats in Los Angeles, learning Italian, or working in the garden.

by Jessica Martin-Weber | Nov 29, 2022 | Infant Care and Breastfeeding
**This is a repost of a classic Informed Pregnancy article.
“It is common to experience some discomfort at latch in the first few weeks of breastfeeding. It should go away as the feeding continues. If it does not end after around 30 seconds, you may need to remove your baby from the breast and reposition her. Break the suction by placing your little finger into the corner of your baby’s mouth and trying to latch again.”
 “I’m really scared of breastfeeding.” Pregnant with her first child, my friend subconsciously rubbed her 34-week belly as I made dinner. I asked her why. She said she’d Googled and learned that breastfeeding could be extremely painful, particularly if she didn’t achieve “the perfect latch.”
She went on to explain that she had read different blogs and forums about how hard it was to get a good latch, stories of women with bleeding nipples and babies who wouldn’t gain weight. She wanted to know the secret to a good latch and what would happen if it didn’t happen for her.
It’s true that many mothers experience some degree of difficulty in the early days of breastfeeding, but here she was, just weeks away from finally meeting her baby, scheduled to take a breastfeeding class and worried sick that she was facing a world of pain if she couldn’t get that elusive latch.
Earlier that same day, I’d had coffee with a good friend, an International Board Certified Lactation Consultant (IBCLC) at a local hospital. When the topic of the “perfect latch” came up, she surprised me by saying that she thought everyone made too big a deal of the latch.
Stay informed and entertained with Dr. Berlin on Instagram!
“If mom isn’t in pain and the baby has plenty of soiled and wet diapers, why do we need to mess with anything? Sure, if there’s a problem like pain or a dehydrated baby, then we need to fix what we can. But so what if that bottom lip is curled in if it’s not causing any bother?” In other words, if it’s comfortable and it’s working, it’s a good latch. There is a wide range of normal. I love this woman; she often says exactly what I’m thinking.
In general, newborn babies are ready to breastfeed and our breasts are ready to feed them. It just works, and we don’t need to mess with it – it doesn’t have to be a complicated endeavor. Yes, for some women breastfeeding is difficult, but we shouldn’t expect trouble. More often than not, moms need support simply because it isn’t all that common in our culture to see a baby at the breast – we cover up or retreat to a restroom to feed, so plenty of women don’t ever see breastfeeding “in action” until it’s their turn to try it!
Many women look online or join a breastfeeding support group for guidance – proactively seeking examples of successful breastfeeding techniques that in other cultures she might have been exposed to from the day she was born. If a new mom doesn’t seek out or have access to that help, she may not even realize that difficulty with pain, bleeding nipples or ineffective milk transfer to her baby could be related to her latch, and there might be a very simple way to “fix” it.
After I shared a few pictures of my then-newborn daughter’s latch on Facebook, I received several emails and comments from other moms stating that they had never seen what a “good latch” looked like, and had endured pain in breastfeeding because they didn’t realize something was wrong.
If you are ever experiencing pain with breastfeeding that is more than a brief moment of discomfort or lasts beyond the initial latch, please seek out help – pain is usually an indicator of a problem that can be corrected. It doesn’t mean you’re doing something wrong, it just means you might benefit from some help.
I talked with my friend Star Rodriguez, IBCLC of Lactastic Services and WIC peer counselor, for the following lists:

When do you need to consider latch issues and improving your nursling’s latch?
- When breastfeeding is painful beyond the initial latching.
- When there is tissue damage to your nipples.
- When there are weight gain issues for the baby.
What latch ‘tips’ can moms try?
- Get into a comfortable position and bring your baby to your level – don’t lean down to theirs.
- Make sure your baby’s body is facing yours, and her arms are not pushing away at you.
- It is best to let the breast fall naturally if possible.
- If you have large breasts OR when your milk first comes in, it may be helpful to hold your breast with your hand.
- Aim your baby’s nose toward the nipple; if it’s necessary to encourage a wider mouth, tickle the very top of the baby’s upper lip with your nipple.
- Your baby’s chin should touch the breast, but her nose should be unobstructed. You should not need to push your breast away from your baby’s nose with a good latch.
- You should be able to hear or see your baby swallowing – short sucks/swallows at first, then longer ones as your milk starts to let down.
- If you’re using a nipple shield, ensure that the nipple and surrounding tissue is being pulled into the shield.
What can a mom do to try to improve a painful or ineffective latch?
- If your baby isn’t opening their mouth wide enough, attempt to show her what to do by opening your own mouth wide. Many babies will subconsciously mimic you.
- Make a “breastwich” – hold your hand in a C-shape behind the areola to help your baby get a bigger mouthful.
- Get your baby as naked as possible for the inviting feeling of skin-to-skin contact.
- Hold your baby securely; a snug, close hold will help.
- Pull your baby in quickly when her mouth is open wide.
- It is common to experience some discomfort at latch in the first few weeks of breastfeeding. It should go away as the feeding continues. If it does not end after around 30 seconds, you may need to remove your baby from the breast and reposition her. Break the suction by placing your little finger into the corner of your baby’s mouth and trying to latch again. Some lactation consultants can show you ways to fix a latch without taking your baby off the breast, but those are easier to learn from being shown rather than told. You may need to put your baby in a different nursing hold or position.
When should a lactation consultant be called?
- If repositioning doesn’t work.
- If you feel sudden soreness after experiencing painless nursing.
- If you feel stabbing or burning pain in your breasts or when your baby latches.
- If you have cracked or bleeding nipples.
- If your latch is not painful, but your baby is not producing a good amount of wet and dirty diapers.
Check out this post by breastfeeding assessment expert Dr. Linda Dahl!
 Jessica Martin-Weber is a writer, speaker and creator of TheLeakyBoob.com. In just four years, The Leaky Boob has become the world’s largest online interactive breastfeeding resource, recommended to mothers by several major hospital networks and health agencies. Jessica is a mother to six fiercely independent daughters and also blogs with her husband, Jeremy, at BeyondMoi.com.

by Shannon Hernandez | Nov 22, 2022 | Infant Care and Breastfeeding
** This is a repost of a classic Informed Pregnancy article.
“Learning how to sleep is similar to teaching a child how to ride a bicycle. It’s new and challenging, for both child and parent. As a parent, you know there’s always a risk of a spill or a scraped knee – but still, you take a deep breath, make sure your child’s helmet is firmly in place, and keep pushing forward.”

With a newborn in the house, sleep becomes a precious luxury. Even a short nap feels incredible, and it’s hard to believe you ever managed to stay awake until 3am in college. With a dull headache and an overwhelming desire for anything that might offer a quick “pick-me-up,” it’s no wonder so many new parents guzzle coffee and lunge for stale donuts (carbs!) in the office break room. Yes, your joy in welcoming a new baby outweighs the pains of exhaustion, but when can you expect some relief? How do you get your baby to sleep soundly when every ‘sleep expert,’ from the authors of the ever-growing number of sleep training books to your mother-in-law, gives you contradictory advice?
As a sleep coach for new parents and new babies, I can reassure you that you are not alone; most parents I work with share the same questions and anxieties about sleep. Here are the five questions I hear most often:
When is the right time to sleep train?
Some babies can sleep through the night from a very young age, but most babies are ready for sleep training when they’re around four or five months old. By this time, they’re usually taking in most of their food during the day, making night-time weaning much easier. Your baby’s fine and gross motor skills have also usually developed enough to assist them with self-soothing.
How long will I need to keep feeding my baby at night?
Assuming you have a healthy baby who was born at term (after your 37th week of pregnancy), you can begin feeding your baby more during the day as early as six weeks after birth. As you gradually get towards the recommended 24 ounces of milk or formula during the day, night feeds can slowly be weaned out. If you’re breastfeeding, you can estimate how much milk your baby is taking in each day by pumping one morning feed and one evening feed, and using the average to estimate your milk supply. You can also use a scale to measure how many ounces your baby is eating at the breast.
Why does my baby keep waking up at night?
If your baby no longer needs night feeds and doesn’t have any medical conditions like acid reflux, teething or a virus, it’s likely she has not yet fully developed her self-soothing skills. It’s normal for all of us – babies and adults – to wake in between sleep cycles. But unlike a new baby, most adults have developed the skills to self-soothe. We roll over on our side, fluff our pillow, kick off our blanket or put another one on. Helping your child learn to self-soothe will help them (and you!) to get back to sleep quickly after waking during the night, and mastering self-soothing will also help your child to feel more confident and independent as she grows.
Stay informed with Dr. Berlin on Instagram!
If I co-sleep, will my baby have a harder time sleeping through the night?
I’ve worked with many parents who co-sleep. Some of them share a family bed for several years, while others plan to co-sleep with their new baby for a few months. Where your baby sleeps is secondary to learning to self-soothe, without interventions such as nursing or being picked up and rocked back to sleep. As your child grows older, where they sleep becomes more important; all children benefit from the security and routine of knowing where they belong when it’s time for bed. But teaching your child to self-soothe is far more vital to getting a better night’s sleep, and can be learned in bed with you.
Is it bad to let my baby cry?
This question always comes up as I work with parents. I believe the answer depends on whether your baby has had all her needs met before being put down to sleep. Learning how to sleep is similar to teaching a child how to ride a bicycle. It’s new and challenging, for both child and parent. As a parent, you know there’s always a risk of a spill or a scraped knee – but still, you take a deep breath, make sure your child’s helmet is firmly in place, and keep pushing forward. You run alongside your child until you feel ready to take the leap and let go as she finds her balance, and it feels amazing to see your child’s joy at riding a bike ‘all on her own.’

All children need to know that their parents or caregivers are there with them, and they are not alone in a new learning process – whether they’re learning to ride a bike or learning how to sleep. I suggest staying with your baby as she learns to sleep, being present and quietly supportive as she learns to self-soothe. When your baby is crying, it’s not easy to resist the urge to intervene – to keep your hands on the bike. But as long as you are there with her, I’d advise you not to hold her back from her personal achievements by interfering with something she’s capable of doing herself. For me, the ultimate answer is no, it’s not ‘bad’ to let your baby cry and fuss during the learning process, but I prefer for babies not to be alone as they struggle to learn and eventually master the skills they need to self-soothe.
I realize I’m yet another of the sleep ‘experts’ I mentioned earlier, and it’s simply not possible to give you personalized advice and work through trial-and-error to find what works for your family and your baby in one short article. Having a sleep coach who is well-educated in child development is key to successfully getting a new family back to sleep. The exhausting days and nights with a sleepless newborn will be over before you know it, but the healthy emotional development you promote will benefit your child throughout her entire life.
Check out this post on asthma and pregnancy by Dr. Nate Fox, MD!
 Shannon Hemandez is a birth coach, postpartum doula and owner of Dream Team Doulas and has served thousands of families in Los Angeles and Orange County over the past 15 years. In 2008 Shannon started sleep coaching after researching infant sleep and child development. Shannon is known as LA’s baby whisperer and she enjoys being the mother of four children that have inspired her in her work to strengthen families. For inquiries write to shannon@dreamteamdoulas.com.

by Susanne Grant | Nov 15, 2022 | Mental Health
**This is a repost of a classic Informed Pregnancy article.
“Taking care of yourself has to be your number one priority. The better you feel the bigger the difference you can make in this world; for yourself, your family and your friends.”

As a hypnobirthing teacher and healing coach I have mums (to-be) coming to me for emotional healing support. Many of us struggle to find our way in this life changing experience; rediscovering ourselves, our bodies and our relationships. Maybe pregnancy and birth didn’t go as you hoped for, leaving behind feelings of failure, guilt or sadness.
This new phase may have brought up old feelings from prior relationships, (sexual) abuse, or other negative experiences, triggering you as you try to continue. I see it time and time again, it is completely normal! These triggers – how overwhelming they may be – create the beautiful opportunity to allow you to find healing. These are my tips to promote emotional healing after pregnancy and birth:
Tip 1: It’s ok, not to be ok!
It begins by acknowledging what you feel is ok. That it is normal to feel like everything isn’t ok. Really, it is ok! Whatever you are feeling right now, tomorrow, or the day after tomorrow, is ok. However, do not ignore it!
Tip 2: Listen
Start paying attention to what triggers you. Is it something that is being said to you? Is it a sound, a smell, a situation that reminds you of something? When you figure out what is your trigger, you need to look at the story behind it. What are you telling yourself? Are you telling yourself you are not good enough? You don’t deserve it? For example, when you get into an argument with your partner for not doing things your way, is it because it makes you feel worthless? Or when you’re not in control, is it because you are scared to lose everything you worked so hard for? It can be helpful to start journaling and writing down what you are experiencing each day.
Stay informed and entertained with Dr. Elliot Berlin, DC!
Tip 3: Self-care needs to be the priority
Taking care of yourself has to be your number one priority. The better you feel the bigger the difference you can make in this world; for yourself, your family and your friends. Don’t be harsh on yourself, if you need to take time off to take care of yourself or your little ones, do it! The world doesn’t end when you say ‘No’ every once in a while! That’s why it is so important for you to start listening to what you need. Do you need more rest? Some alone time? Or do you need someone to help you? Remember, knowing your boundaries isn’t a sign of failure! Allow yourself, and others, to take care of you.

Tip 4: Start EFT
The Emotional Freedom Technique (EFT) or “tapping” is a great and gentle tool to help you release those trapped feelings that you just can’t seem to get rid of. Tapping on specific points of the body, it will help to releasing the blockages within the energy system which are the source of emotional intensity and discomfort you have been feeling. That is why it is so important you need to start listening to what is bothering you and where it shows up in your body. When you do, and start giving it the attention it deserves it will start shifting. When you use EFT on top of this it will promote the healing even further. You may need to do a few repetitions; you may need to do it for a few minutes each day for the next for days or weeks. Just keep going until it’s completely gone!
Postpartum recovery takes time, so give yourself the time you deserve. Take as much rest as you need and make sure you find a balance that works for you with plenty of water and nurturing foods. If you still feel like you are not feeling well, please tell someone. Talk to a friend, colleague, or family member. You are not alone!
Check out this new parenting blog post for tips on housework for kids!

Susanne is an international Hypnobirthing & Healing coach who specializes in (birth) trauma, PTSD & body issues. She coaches women around the world to heal sexual abuse & trauma as well as prior traumatic births. While pregnant, Susanne’s experience of child abuse put her on a different road of care from her team of midwives. This gave her a new mission in life, helping women heal wounds from the past. Having been diagnosed with PTSD at 17, she knows firsthand how challenging this can be.
For support pre or post birth, and her free Heal Yourself Workshop, please visit www.grantmethod.com or email her at susanne@grantmethod.com

by Dr. Alyssa Berlin | Oct 25, 2022 | Family and Relationships, Mental Health
“Let’s all agree that unilaterally, parents typically mean well and truly have your best interests at heart. That being said, after having a baby, chances are that your parents fit into one of two categories: there is the “I love you…you are amazing…I could not have done it without you” (we will call that category A), and then there is the “I love you, but you are making me crazy, and if you don’t get out of my face and give me some space I am going to scream” (category B). ”
The old saying: “You can’t live with ’em, you can’t live without ’em” must have been referring to parents/in-laws. Nothing challenges your relationship with your parents more than joining the ranks and becoming parents! Yikes! I am one of them.
Having a child often shines a spotlight on both the positive and negative experiences and feelings that you have towards your own parents. Becoming a parent can serve as catalyst for bonding with your parents in a new way, or it can serve as a direct reminder of the ways that mom and dad may have neglected to be the parent you were wanting.
The postpartum period, however, is not a good time to remind mom and dad about all the ways they may have failed you and how you are going to do better with your child. So if you are noticing some of those feelings come to the surface, pregnancy is a wonderful time to explore and work through those experiences before your baby arrives.
Let’s all agree that unilaterally, parents typically mean well and truly have your best interests at heart. That being said, after having a baby, chances are that your parents fit into one of two categories: there is the “I love you…you are amazing…I could not have done it without you” (we will call that category A), and then there is the “I love you, but you are making me crazy, and if you don’t get out of my face and give me some space I am going to scream” (category B).

The problem is that oftentimes you will not know which category your parents belong to until after your baby is born. Then it might be too late – you already committed yourself to having your mom move in with you, sleep on the couch, and be there 24/7 for the first 6 weeks of your baby’s life. (Insert scream here).
When you find yourself with category A parents – you are in luck. Embrace them and revel in the support they can offer you as you adjust to motherhood. Remember that there is nothing wrong with accepting help. In my opinion, it is the strong women that can utilize help from others, recognize that they are a part of a village, and do not have to do it all alone. There is not a special award given out to women who feel a need to prove that one day post delivery they can be superwoman. It doesn’t exist, so relax and enjoy the helping hands around you.
There are usually clues along the way that you may have a category B parent on your hands. I want you to remember that right after you have a baby, you are feeling vulnerable and emotional. You will likely not be feeling your best or in the mood to entertain any high maintenance, not self-sufficient guests. You will probably be looking to surround yourself with safe people who won’t take your mood changes, pointed comments, or emotional moments personally and will be empathic of your need to recover from birth and appreciate the emotional magnitude of your journey to parenthood.
Follow Dr. Alyssa Berlin, PsyD on Instagram!
So, if your parents are typically high maintenance, needy people who like to be catered to, chances are they are going to fall in the latter category and might not be an optimal choice to play a major role on your postpartum care team. Situations tend to get more stressful after having a baby, not less. So, if under the best of situations, an evening out with the folks usually results in you needing a stiff drink and an ice pack, then….you guessed it – great contenders for category B and an awful contender for a long-term post birth houseguest.
That doesn’t mean that mom and dad don’t have a role in the process. It simply means you want to think about the situation more strategically and please, I am begging you, don’t have them sleep on your couch or in a second bedroom in your house. There are wonderful hotels/motels or awesome friends that would be happy to host your parents so that you can enjoy the best of both worlds: quiet time alone as well as nice visits with mom and dad.
They may, however, make great people to run errands, do the food shopping, pick up dry cleaning, and other valuable contributions to your postpartum experience in a less hands-on way. As you envision your postpartum experience, it is advisable to think about everyone’s strengths and how they will be most helpful to you during this special time. Yup, you guessed it; this time is all about you and what you need in the moment to ensure that you have the best possible start to motherhood.

If one parent has a particular skill in cooking, assign them to cooking duty. If another parent enjoys shopping, they get shopping duty and everyone can pick straws for cleaning duty. Sit down with your partner while you are still pregnant and jot down a list of daily activities/errands that have to get done as well as some of your favorite recipes. You can disseminate the various tasks to different people or leave the list on the refrigerator. And in the absence of parents or in-laws, there are other wonderful people: doulas, nurses and professional services, drop off and delivery services, and cleaning services around you that will be happy to be a part of your village and postpartum team.
One last note: if during the pregnancy, you already have strong thoughts regarding what you may or may not want from your parents or what role you may or may not want them to play, I strongly recommend you share it with them before the baby’s birth. This will alleviate a lot of stress on you after the birth and will likely give them a better chance to honor your requests.
You have a plan for birth, now make sure you plan for what comes after. Click for more info!

Dr. Alyssa Berlin is a clinical psychologist specializing in pregnancy, postpartum, and parenting. She offers private counseling for women individually and with their partners. Dr. Berlin is the creator of The AfterBirth Plan™, a program that prepares couples for what to expect after a baby is born. The workshop teaches couples how to prepare for a healthy postpartum transition for the baby, for each partner, and for the evolving relationship. She combines her psychological background and her doula training to help women and their partners feel empowered and comfortable in the labor and delivery process, both on a physical and emotional level. Dr. Berlin has specific expertise addressing fear and anxiety that may arise before, during, or after birth.
Dr. Berlin is on the Board of Advisors for the International Cesarean Awareness Network (ICAN) and is a faculty member of Maternal Mental Health NOW Training Institute. She conducts live pregnancy and parenting workshops throughout Southern California and online. You can read Dr. Alyssa’s blogs on the Huffington Post where she contributes to PBS’s ‘This Emotional Life” project. Dr. Berlin received her doctorate degree at Argosy University in Atlanta, GA and went on to become a certified Gottman educator. She is a member of the American Psychological Association. She and her husband, prenatal chiropractor Dr. Elliot Berlin, live in Los Angeles and are the proud parents of four amazing children.

